

Roux-en-Y Gastric Bypass in Delhi
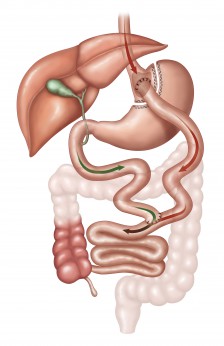 Gastric bypass surgery is a procedure that creates a small pouch in the upper most part of the stomach to restrict food intake. The stomach pouch is then connected to lower segment of the small intestine, bypassing the duodenum (the first part of the small intestine) and some of the jejunum (the second part of the small intestine), delaying the mixing of ingested food and the digestive enzymes.
The net effect of this re-arrangement is a restricted intake of food and due to the bypass, some malabsorption- both of these leading to weight loss. However it is not only the restriction and malabsorption that leads to weight loss and correction of the co-morbidities in obese people. The intestines secrete a number of hormones specially when exposed to undigested food directly in their lumen that control and modify the metabolism in our body to correct diabetes, control blood pressure and also control hunger. These hormones also increase our resting metabolic rate thereby increasing energy consumption even at rest.
Roux-en- Y Gastric Bypass (RYGB) Surgery in India is almost always done laparoscopically and is still the “Gold standard” in the world. All other procedures are usually compared to this when it comes to the results in terms of excess weight loss and resolution of co-morbidities.
What Is Roux-en-Y Gastric Bypass?
Roux-en-Y Gastric Bypass is performed by creating a small pouch from the upper part of the stomach. A section of the small intestine is then connected directly to this pouch.
The remaining stomach continues to produce digestive juices but no longer receives food directly. These digestive juices later mix with food further down the intestine, creating the characteristic Y-shaped intestinal reconstruction from which the procedure gets its name.
How Does Gastric Bypass Help With Weight Loss?
Roux-en-Y Gastric Bypass works through several mechanisms:
- Smaller stomach capacity
- Earlier feeling of fullness
- Changes in appetite-related hormones
- Altered food passage through the intestine
- Reduced absorption of some nutrients
- Improved insulin sensitivity and metabolic function
The procedure should not be described as working only through “restriction and malabsorption.” Changes in gastrointestinal hormones and metabolism are also important contributors to its effects.
Who May Be Considered for Gastric Bypass?
Suitability is determined after a complete bariatric assessment.
Factors may include:
- BMI
- Type 2 diabetes
- High blood pressure
- Sleep apnea
- Fatty liver disease
- Gastroesophageal reflux disease
- Previous weight-loss attempts
- Eating behaviour
- Previous abdominal or bariatric surgery
- Nutritional status
- Ability to follow long-term dietary and medical recommendations
Current Indian OSSI guidance recognizes RYGB as a standard bariatric and metabolic procedure and uses lower BMI thresholds for Asian patients because metabolic complications may occur at lower BMI levels.
Potential Benefits of Roux-en-Y Gastric Bypass
In appropriately selected patients, potential benefits may include:
- Significant and sustained weight reduction
- Improvement in type 2 diabetes
- Better blood-pressure control
- Improvement in sleep apnea
- Improvement in abnormal cholesterol levels
- Improvement in fatty liver disease
- Better mobility
- Improvement in several obesity-related health conditions
Results differ between patients, so fixed weight-loss or disease-remission percentages should not be guaranteed.
Gastric Bypass and Type 2 Diabetes
RYGB can produce important improvements in blood-sugar control.
Changes in insulin sensitivity and gastrointestinal hormones may begin before maximum weight loss occurs. Some patients may be able to reduce diabetes medicines under medical supervision, while others may continue to need treatment.
Use “diabetes remission” rather than “permanent cure,” because diabetes may recur later.
Gastric Bypass and Acid Reflux
Roux-en-Y Gastric Bypass may be considered for selected patients who have obesity along with significant gastroesophageal reflux disease.
ASMBS notes that gastric bypass often improves reflux symptoms. However, procedure selection should still be individualized according to the patient’s symptoms, anatomy and medical condition.
Roux-en-Y Gastric Bypass vs Sleeve Gastrectomy
Roux-en-Y Gastric Bypass
- Creates a small gastric pouch
- Reroutes part of the intestine
- Produces strong metabolic effects
- Requires long-term nutritional monitoring
- May be considered in selected patients with significant reflux
Sleeve Gastrectomy
- Removes a large portion of the stomach
- Does not reroute the intestine
- Reduces stomach capacity
- Influences appetite-related hormones
- May be suitable for other patient profiles
There is no single bariatric operation that is best for every patient.
Risks and Considerations of Gastric Bypass
Possible early risks include:
- Bleeding
- Infection
- Leakage
- Blood clots
- Anaesthesia-related complications
Possible long-term concerns may include:
- Iron deficiency
- Vitamin B12 deficiency
- Calcium or vitamin D deficiency
- Marginal ulcers
- Dumping syndrome
- Internal hernia
- Bowel obstruction
- Weight regain
- Need for revision in selected cases
RYGB carries greater risk of certain vitamin and mineral deficiencies than sleeve gastrectomy, which makes long-term supplementation and monitoring important.
What Is Dumping Syndrome?
Dumping syndrome can occur when food, particularly meals containing a large amount of sugar, moves rapidly from the stomach pouch into the small intestine.
Symptoms may include:
- Nausea
- Abdominal discomfort
- Sweating
- Dizziness
- Rapid heartbeat
- Weakness
- Diarrhoea
Following the recommended bariatric diet can help reduce these symptoms.
Nutritional Follow-Up After Gastric Bypass
Patients generally require long-term nutritional monitoring after RYGB.
Follow-up may include:
- Complete blood count
- Iron and ferritin
- Vitamin B12
- Folate
- Vitamin D
- Calcium
- Protein levels
- Other micronutrients when required
ASMBS patient guidance also emphasizes lifelong vitamin supplementation and regular laboratory monitoring after bariatric surgery.
Recovery After Roux-en-Y Gastric Bypass
RYGB is commonly performed laparoscopically.
Patients are usually encouraged to start walking early after uncomplicated surgery. Diet is gradually advanced according to the bariatric team’s protocol.
Typical diet stages may include:
- Clear liquids
- Full liquids
- Pureed or soft foods
- Gradual introduction of solid foods
Long-term diet focuses on adequate hydration, protein intake, portion control and appropriate vitamin supplementation.
Life After Gastric Bypass
Long-term success requires continued medical and lifestyle follow-up.
Patients should focus on:
- Small portion sizes
- Eating slowly
- Adequate protein
- Proper hydration
- Limiting high-sugar foods
- Regular physical activity
- Taking prescribed supplements
- Periodic blood tests
- Regular bariatric follow-up
Weight-loss surgery is an important treatment tool, but obesity remains a chronic condition requiring ongoing management.
Can Weight Come Back After Gastric Bypass?
Yes. Some weight regain can occur after surgery.
Possible contributing factors include eating patterns, reduced activity, metabolic factors, anatomical changes and progression of obesity as a chronic disease.
Weight regain should be properly evaluated because management may involve nutritional, behavioural, medical, endoscopic or surgical treatment depending on the cause.
Why Consult Dr. Sushant Wadhera for Roux-en-Y Gastric Bypass in Delhi?
Dr. Sushant Wadhera provides evaluation and surgical treatment planning for patients considering Roux-en-Y Gastric Bypass and other bariatric procedures in Delhi.
Procedure selection is based on the patient’s BMI, obesity-related conditions, diabetes status, reflux symptoms, eating habits, nutritional status, previous surgery and overall health rather than recommending the same operation to every patient.
Dr. Sushant Wadhera
MBBS, MS (General Surgery), FNB (Minimal Access Surgery)
Bariatric, Laparoscopic & General Surgeon
Frequently Asked Questions
1. What is Roux-en-Y Gastric Bypass?
Roux-en-Y Gastric Bypass is a bariatric procedure in which a small stomach pouch is created and connected to a lower part of the small intestine to support weight loss and metabolic improvement.
2. How does gastric bypass help with weight loss?
It works through reduced stomach capacity, changes in food passage, altered nutrient absorption and hormonal effects that influence hunger, fullness and metabolism.
3. Who may be suitable for gastric bypass?
Suitability depends on BMI, obesity-related conditions, diabetes, reflux symptoms, previous treatment, nutritional health and overall surgical fitness.
4. Can gastric bypass help with type 2 diabetes?
Yes. RYGB can significantly improve blood-sugar control in many patients with obesity and type 2 diabetes. Some patients may achieve diabetes remission.
5. Can gastric bypass improve acid reflux?
Yes. RYGB can improve reflux symptoms in many selected patients and may be considered when obesity and significant GERD occur together.
6. Is gastric bypass better than sleeve gastrectomy?
Neither procedure is automatically better. The choice depends on BMI, diabetes, reflux, eating behaviour, medical history and nutritional status.
7. What are the risks of Roux-en-Y Gastric Bypass?
Possible risks include bleeding, infection, leakage, blood clots, nutritional deficiencies, ulcers, dumping syndrome, internal hernia and bowel obstruction.
8. Will I need vitamins after gastric bypass?
Yes. Long-term vitamin and mineral supplementation is generally required, along with periodic blood tests.
9. What is dumping syndrome?
Dumping syndrome occurs when food moves rapidly into the small intestine and can cause nausea, sweating, weakness, abdominal discomfort, dizziness or diarrhoea.
10. How long does recovery take after gastric bypass?
Recovery varies between patients. Patients usually begin walking early and gradually progress through a structured diet and activity plan.
11. Can weight come back after gastric bypass?
Yes. Some weight regain is possible, which is why long-term nutritional, lifestyle and medical follow-up remains important.
12. Is Roux-en-Y Gastric Bypass performed laparoscopically?
Yes. RYGB is commonly performed using minimally invasive laparoscopic techniques in suitable patients.
13. Can gastric bypass be reversed?
Reversal is technically possible in selected circumstances, but it is a complex procedure and is not considered a routine option.
14. What is the difference between RYGB and Mini Gastric Bypass?
RYGB creates a Y-shaped reconstruction with two intestinal connections, while Mini Gastric Bypass or OAGB generally uses one main stomach-to-intestine connection.
15. Who should I consult for gastric bypass in Delhi?
Patients considering gastric bypass can undergo a complete bariatric evaluation. Dr. Sushant Wadhera provides assessment and treatment planning for Roux-en-Y Gastric Bypass in Delhi.
